Mr Vittorio Russo specialises in the diagnosis and treatment of spinal disorders affecting the cervical spine, thoracic spine and lumbar spine.
His practice encompasses both common degenerative conditions and highly complex spinal pathology, including spinal tumours, spinal deformity, revision spinal surgery, cranio-cervical junction disorders and advanced spinal reconstruction.
Patients are frequently referred for complex diagnostic problems, failed previous treatments and highly specialised tertiary pathology. Equally, common conditions such as neck pain, back pain and sciatica can often be managed successfully through conservative treatment strategies.
Every patient receives an individualised assessment, with recommendations tailored to their symptoms, neurological findings, imaging results, overall health, lifestyle and personal goals.
Cervical disc degeneration, disc prolapse, foraminal stenosis and spondylosis can affect the discs, joints and nerves within the neck.
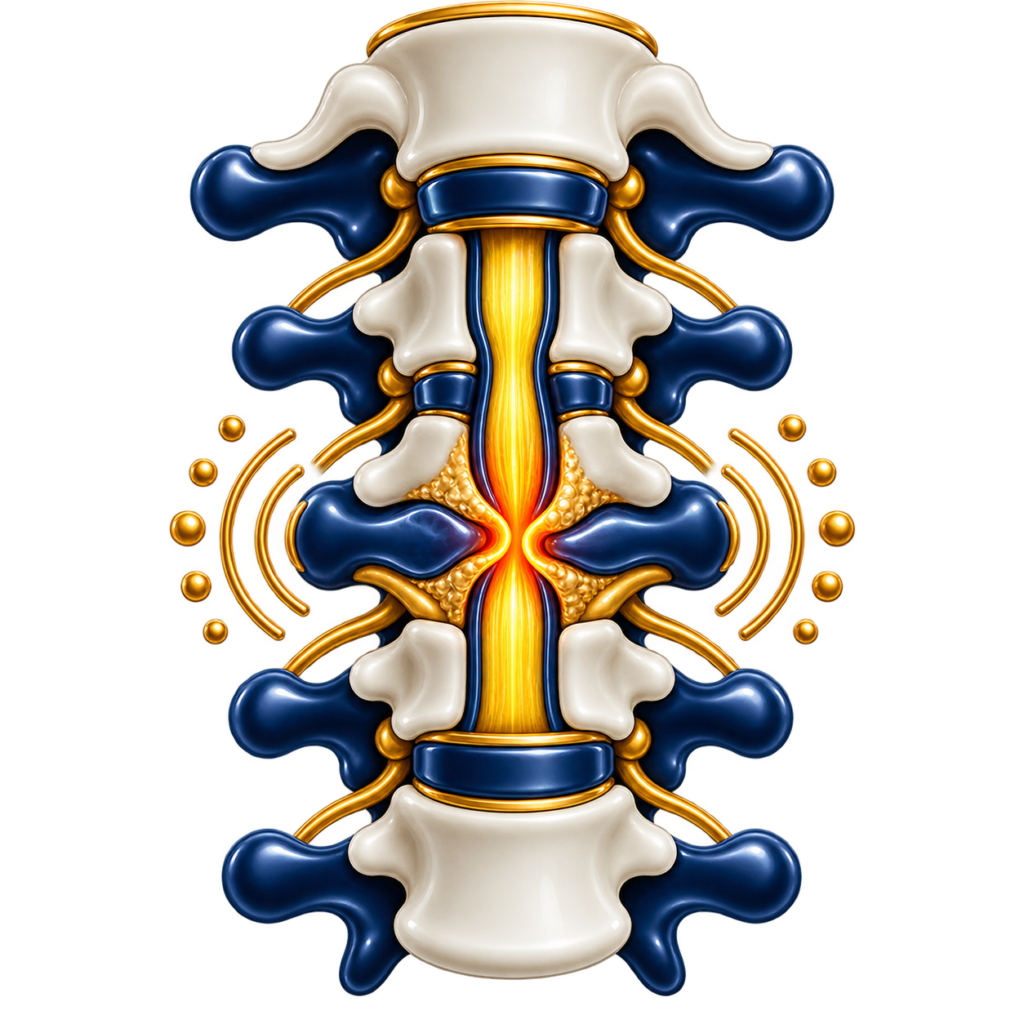
Cervical myelopathy occurs when compression of the spinal cord within the neck begins to affect neurological function.
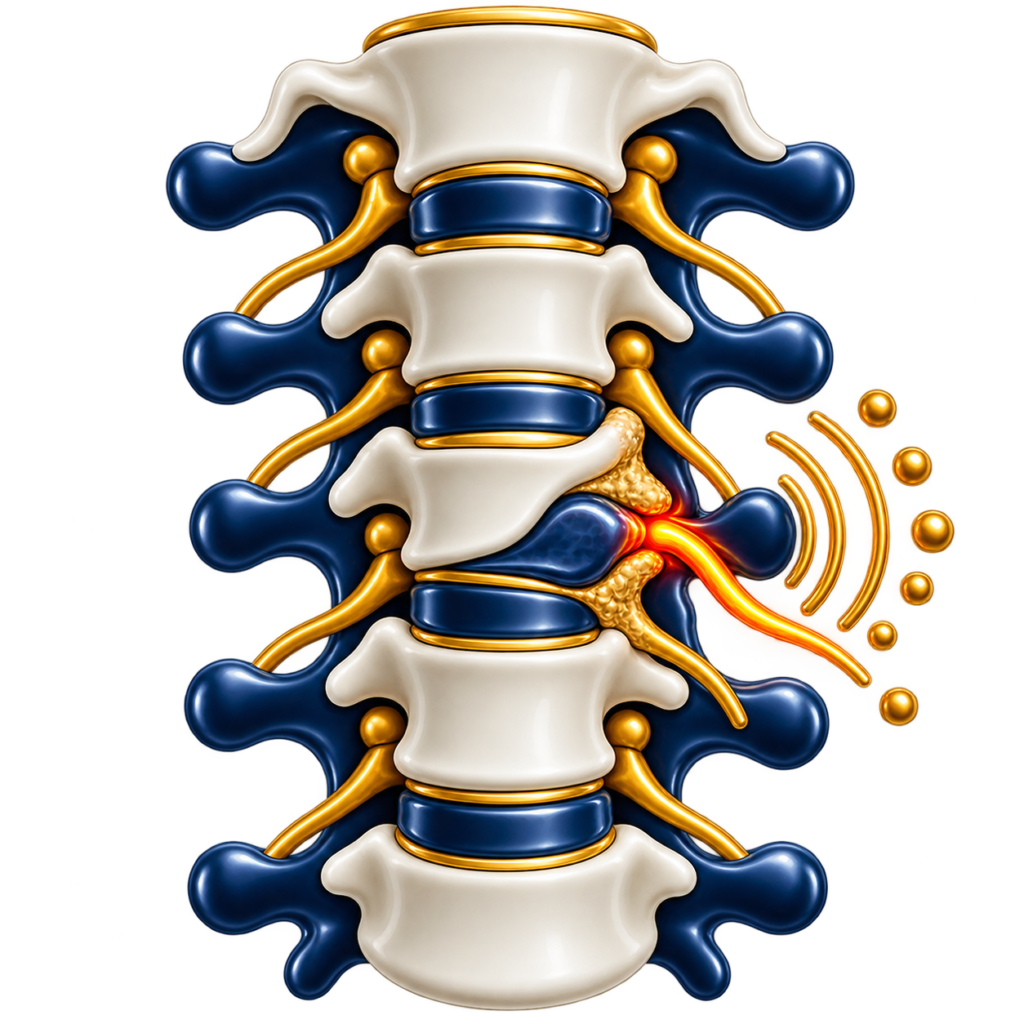
Compression or irritation of a nerve exiting the cervical spine may cause symptoms extending into the shoulder, arm or hand.
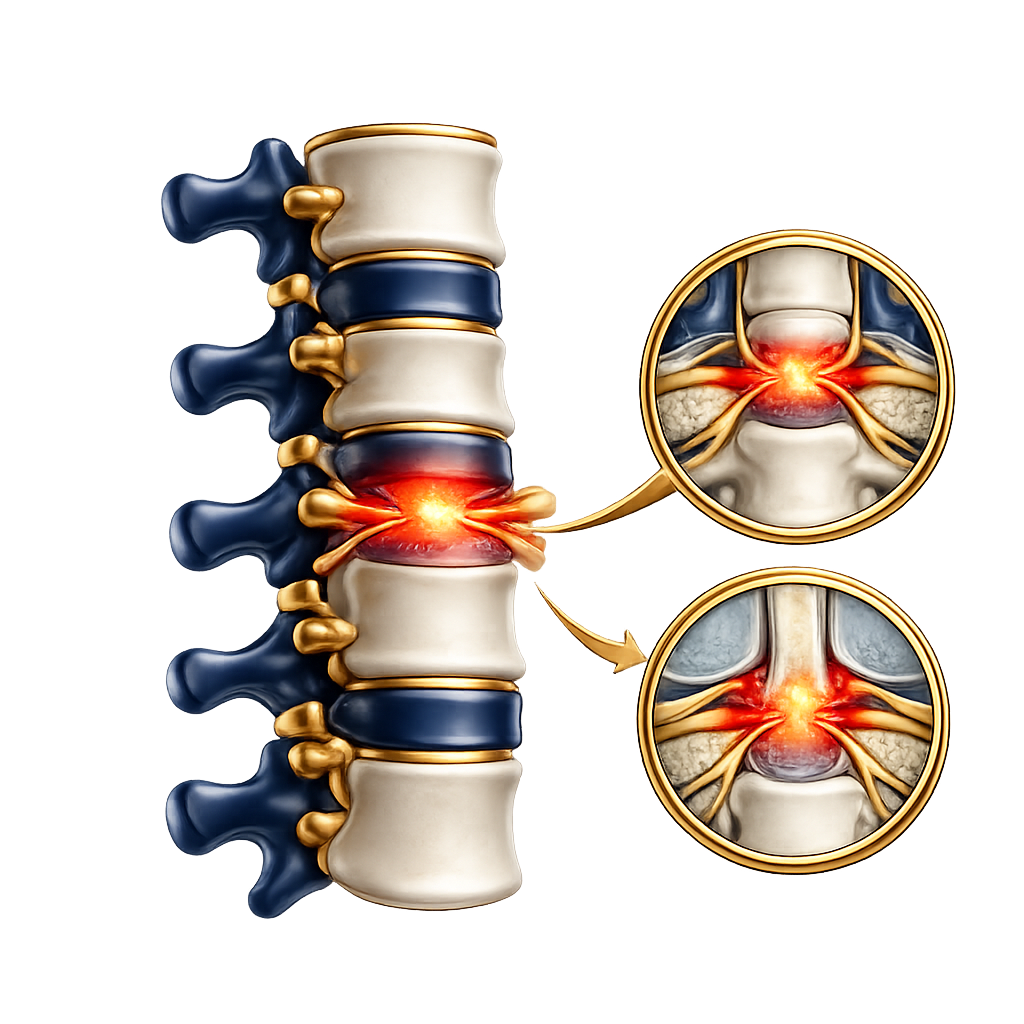
Lower back pain may arise from degenerative changes, joint problems, spinal instability or persistent symptoms following previous surgery.
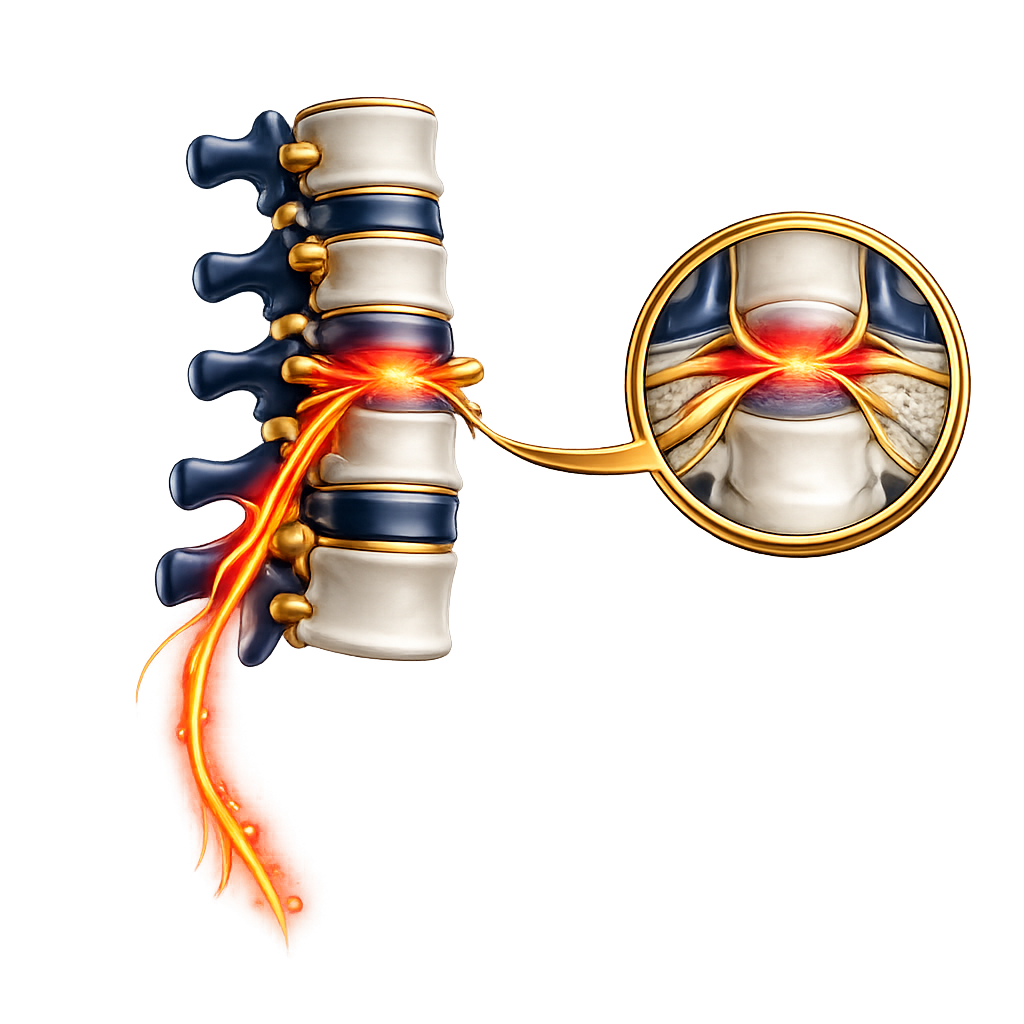
Sciatica is pain radiating down the leg due to irritation or compression of a spinal nerve, most commonly caused by a lumbar disc prolapse.
Lumbar spinal stenosis occurs when narrowing of the spinal canal compresses nerves within the lower back.
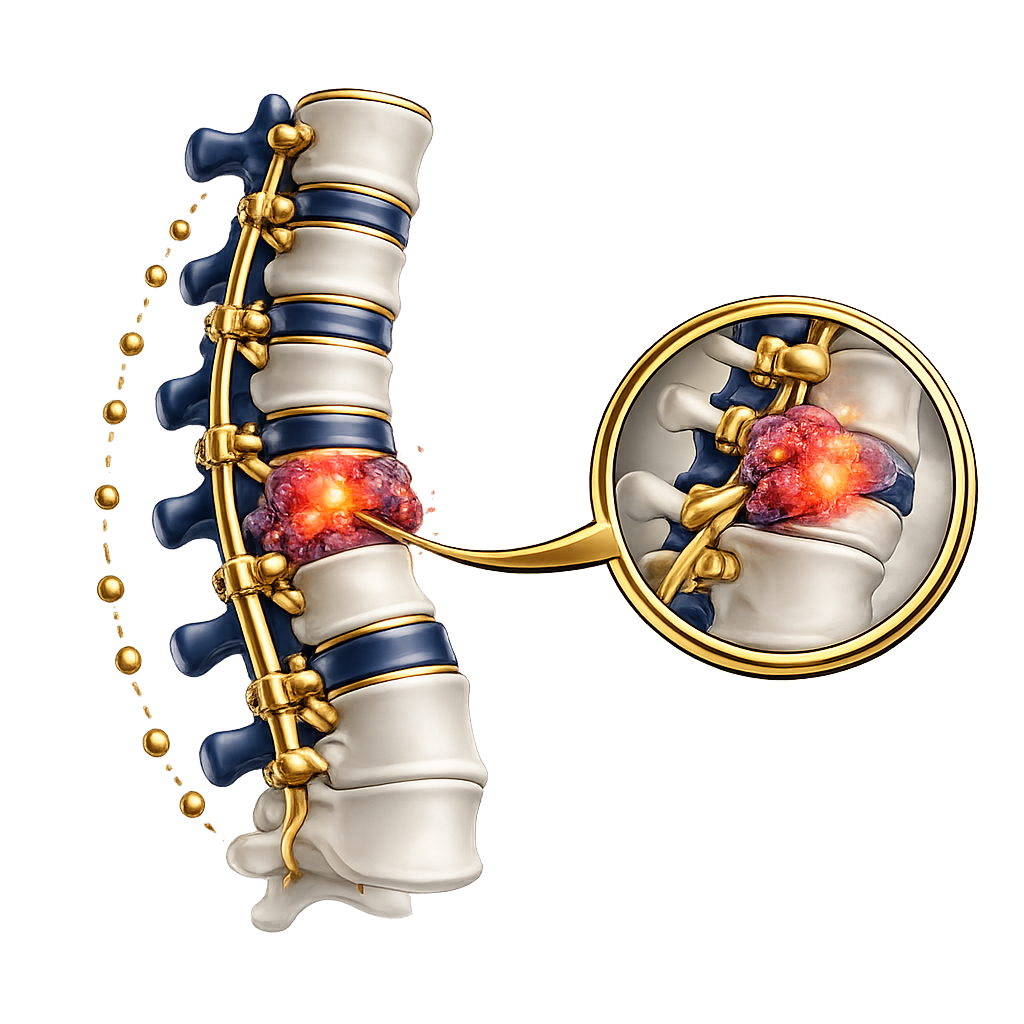
Primary and metastatic spinal tumours may affect different structures within and around the spine and often require multidisciplinary oncology care.
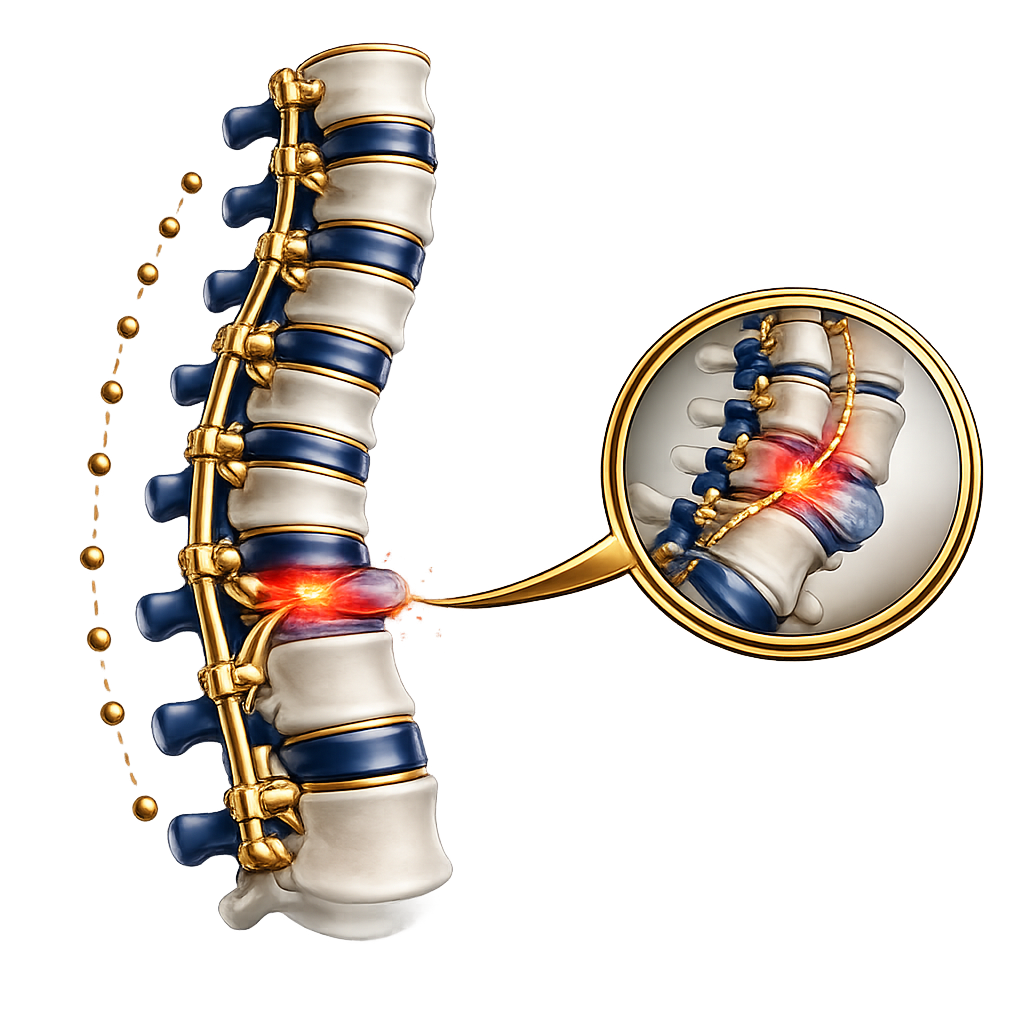
Adult spinal deformity may result from degenerative changes, previous surgery, trauma, infections or other spinal conditions.
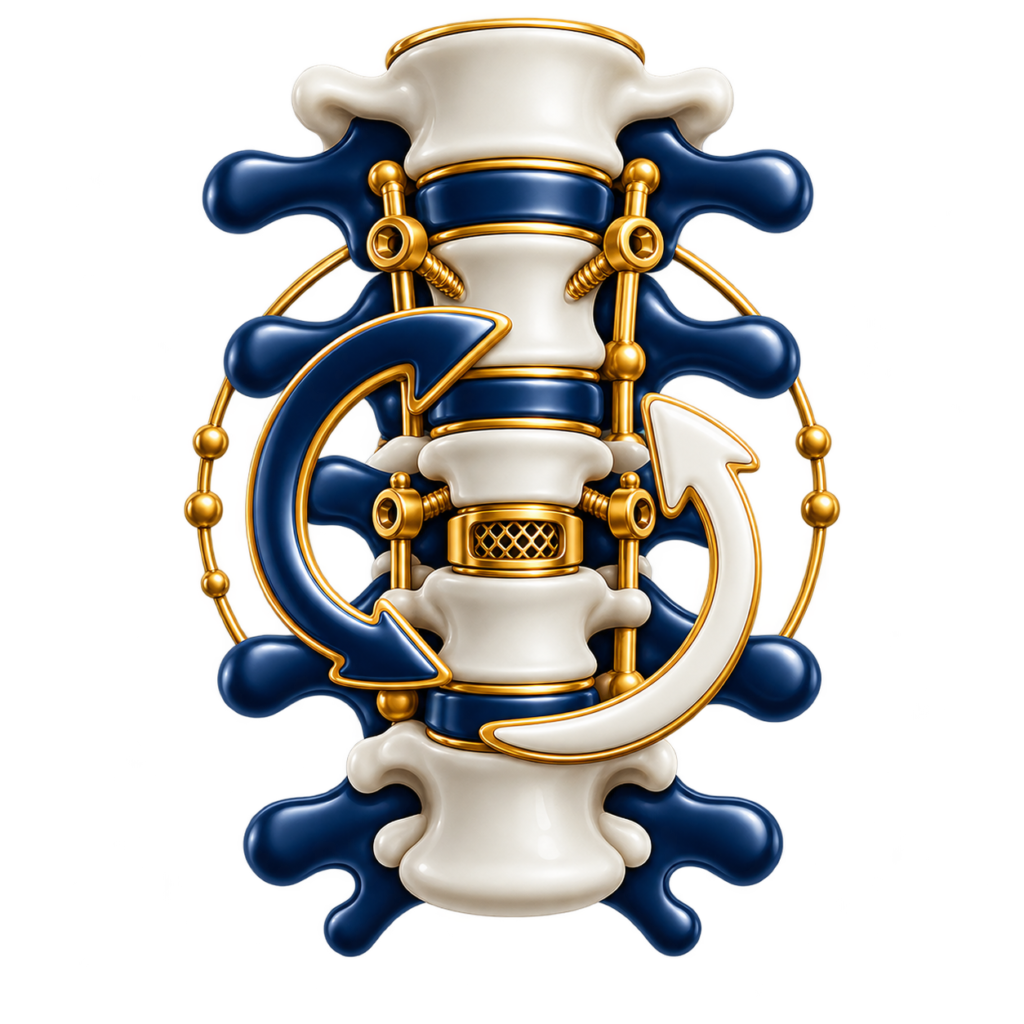
Revision surgery refers to spinal procedures performed following previous spinal operations and requires detailed investigation and specialist planning.
These disorders affect the specialised region where the skull meets the upper cervical spine.
Spinal fractures and traumatic injuries may follow falls, accidents, sporting injuries or osteoporosis-related collapse.
Symptoms, neurological findings, imaging results and personal circumstances are considered together to establish the diagnosis and most appropriate treatment pathway.
Where appropriate, Mr Russo works with physiotherapists, pain specialists, radiologists, oncologists, rehabilitation teams and other healthcare professionals.
Options may include specialist physiotherapy, rehabilitation, pain management, spinal injections, activity modification and minimally invasive interventions.
When surgery is required, the aim is to use the least invasive effective technique while providing the specialist expertise needed to manage complex spinal pathology.

Not necessarily. If you already have MRI or CT imaging, clinic letters or previous reports, these may be shared in advance. If imaging or other investigations are required, they can be arranged promptly through affiliated specialist centres.
Not necessarily. Many spinal conditions can be managed successfully with physiotherapy, rehabilitation, pain management, spinal injections or activity modification. Surgery is considered only where appropriate, following careful assessment of your symptoms, neurological findings, imaging and personal goals.
Depending on your condition, further investigations may include MRI, CT imaging, dynamic X-rays, EMG or nerve conduction studies, SPECT-CT, nuclear medicine imaging or vascular imaging. Tests are requested where they can help clarify the diagnosis or guide treatment planning.
Mr Russo treats the full spectrum of cervical, thoracic and lumbar spinal conditions. These range from neck pain, back pain, sciatica and degenerative disorders to spinal tumours, deformity, revision surgery, cranio-cervical junction disorders, spinal trauma and complex reconstruction.
Yes. Mr Russo regularly assesses patients seeking specialist second opinions, including those with persistent symptoms, previous spinal surgery, failed treatments, complex diagnostic problems or possible revision surgery. Both surgical and non-surgical options are considered.